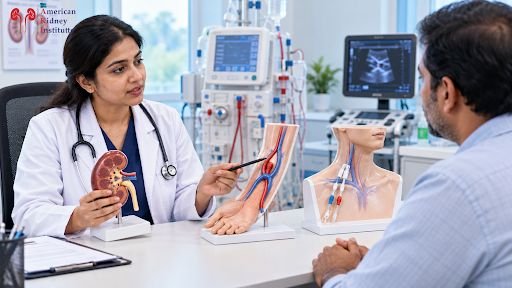
Which Is Better for Dialysis: Catheter or AV Fistula? A Complete Guide
Starting hemodialysis is a major change in a patient’s life. Along with understanding the dialysis process, one of the most important decisions is choosing the right vascular access.
Vascular access is the route through which blood leaves the body, travels to the dialysis machine for cleaning, and returns to the bloodstream. Without reliable vascular access, hemodialysis cannot be performed effectively.
The two options patients commonly hear about are a dialysis catheter and an AV fistula. Although both can provide access for hemodialysis, they are very different in how they are created, how quickly they can be used, and the risks associated with them.
For many patients who are expected to need long-term hemodialysis, an AV fistula is generally preferred because it usually has fewer complications and better long-term durability than a central venous catheter. However, a catheter can be extremely useful when dialysis needs to begin urgently or when a fistula or graft is not suitable.
For patients looking for a Kidney Specialist in Vijayawada, understanding these differences can make conversations about dialysis planning much easier.
What Is Vascular Access for Hemodialysis?
During hemodialysis, blood needs to move from the patient’s body to a dialysis machine.
The machine passes the blood through a special filter called a dialyzer, where waste products and excess fluid are removed. The cleaned blood is then returned to the body.
A vascular access provides this connection between the patient’s bloodstream and the dialysis machine.
There are three major types of hemodialysis vascular access:
- AV fistula: A surgeon connects an artery and a nearby vein, usually in the arm, creating a stronger blood vessel that can later be used for dialysis needles.
- AV graft: A special tube is used to connect an artery and vein when the patient’s own blood vessels are not suitable for a fistula.
- Dialysis catheter: A soft tube is placed into a large vein, commonly in the neck or chest, allowing blood to be taken from and returned to the body without placing needles into an AV access.
Each option has a role, but they are not interchangeable in every situation.
What Is an AV Fistula?
An arteriovenous fistula, commonly called an AV fistula or simply a fistula, is a surgically created connection between an artery and a nearby vein.
It is usually created in the arm.
The connection allows arterial blood flow to enter the vein, causing the vein to become larger and stronger over time. Once the fistula has matured sufficiently, dialysis needles can be placed into it during hemodialysis.
An AV fistula uses the patient’s own blood vessels rather than an artificial tube.
This is one of the major reasons it is generally preferred for long-term hemodialysis when it is medically suitable. The National Kidney Foundation describes a fistula as the preferred access because it generally has fewer problems and lasts longer than other access types.
What Is a Dialysis Catheter?
A dialysis catheter is a soft, flexible tube placed into a large vein.
For hemodialysis, the catheter is commonly placed in a large vein in the neck, although other sites may be considered depending on the patient’s circumstances.
Unlike a fistula, the catheter does not require the patient to wait for the access to mature before it can be used.
This makes it particularly useful when dialysis needs to start urgently.
For example, a patient who develops severe acute kidney injury and suddenly requires dialysis may not have enough time to wait for a fistula to mature. In such situations, a catheter may provide immediate access.
However, because the catheter enters a large vein and has an external component, it carries higher risks of infection and other access-related complications than a well-functioning AV fistula.
AV Fistula vs Dialysis Catheter: Which Is Better?
For a patient who needs long-term hemodialysis and has suitable blood vessels, an AV fistula is generally preferred over a dialysis catheter.
This does not mean that a catheter is a “bad” option.
A catheter can be the right option in an emergency, during the period before a fistula is ready, or when an AV fistula or graft cannot be created.
The difference is mainly about the intended duration, patient’s condition, vascular anatomy, and urgency of dialysis.
A fistula generally offers better long-term durability and a lower risk of infection than a catheter. A catheter, on the other hand, provides rapid access and does not require maturation.
Why Is an AV Fistula Preferred for Long-Term Dialysis?
There are several reasons why an AV fistula is generally preferred when it is appropriate for the patient.
Lower Infection Risk
One of the major advantages of a fistula is the lower risk of bloodstream infection compared with a dialysis catheter.
A catheter creates a direct pathway through the skin into a large vein. Because part of the catheter remains outside the body, strict infection-control practices are essential.
A mature fistula is completely under the skin between dialysis sessions.
This does not mean that a fistula can never become infected, but its infection risk is generally lower than that of a central venous catheter.
Better Long-Term Durability
An appropriately functioning AV fistula can provide vascular access for a long period.
Because it is created using the patient’s own blood vessels, it does not depend on a synthetic tube or an external catheter.
However, fistulas can develop problems such as narrowing, clotting, aneurysmal changes, or failure to mature. Regular monitoring helps identify these issues early.
Good Blood Flow
A mature fistula is designed to provide the blood flow needed for hemodialysis.
During dialysis, two needles are typically placed into the fistula. One needle allows blood to travel toward the dialysis machine, while the other returns the cleaned blood to the patient.
Good blood flow is important for delivering an effective dialysis treatment.
Why Is a Dialysis Catheter Used?
Although fistulas are generally preferred for long-term access, dialysis catheters remain very important.
The biggest advantage is immediate usability.
A catheter can generally be used for dialysis once it has been appropriately placed and cleared for use.
A fistula, in contrast, needs time to mature.
This difference becomes particularly important when dialysis must begin urgently.
For example, a patient admitted with severe AKI, dangerous potassium elevation, severe fluid overload, or another urgent indication for dialysis may need treatment before a permanent access can be created.
In that situation, waiting several weeks for a fistula to mature may not be practical.
A catheter can provide access while the patient’s kidney function is assessed and while a longer-term access plan is developed.
What Does “Fistula Maturation” Mean?
Creating an AV fistula is only the first step.
The vein needs time to adapt to the increased blood flow coming from the artery.
Over time, the vein generally becomes larger and its wall becomes stronger, making it more suitable for repeated dialysis needle placement.
This process is called fistula maturation.
The time required can vary significantly between patients.
A fistula may be ready for use after several weeks, but some fistulas take longer or require additional procedures before they become suitable for dialysis. The KDOQI guideline defines maturation as the process by which an AV fistula becomes suitable for providing the prescribed dialysis treatment.
This is why planning vascular access before dialysis becomes urgently necessary is so important.
Why Should a Fistula Be Planned Early?
If a patient has advanced CKD and the nephrologist expects dialysis may be required in the future, vascular access planning should not be postponed until the last minute.
Creating a fistula requires evaluation of the patient’s blood vessels and a procedure by an appropriately trained vascular access surgeon.
The fistula then needs time to mature.
If dialysis suddenly becomes necessary before the fistula is ready, a catheter may have to be used temporarily.
Early planning can therefore reduce the likelihood of starting long-term dialysis with a catheter when a fistula would otherwise have been possible.
For patients under the care of a Kidney Specialist in Vijayawada, discussing vascular access early can be an important part of preparing for possible future dialysis.
What Happens If a Fistula Does Not Mature?
Not every fistula matures successfully.
Sometimes the vein may not enlarge enough or the blood flow may not be adequate for dialysis.
There can also be narrowing or other structural problems affecting the access.
When this happens, the vascular access team may investigate the cause using physical examination, ultrasound, or other appropriate tests.
In some cases, an additional procedure may help improve the fistula.
If the patient’s blood vessels are not suitable for a fistula, an AV graft may be considered.
A graft connects an artery and vein using a special tube placed under the skin. It is another established form of hemodialysis access.
What Are the Disadvantages of a Dialysis Catheter?
A catheter provides important benefits, but it also has several disadvantages.
Higher Infection Risk
Catheter-related infections can become serious because the catheter provides direct access to the bloodstream.
Fever, chills, redness, drainage, or other signs of infection should be reported immediately to the dialysis or medical team.
Catheter care requires careful attention to sterile technique and dressing management.
Risk of Blockage or Poor Blood Flow
A catheter may develop problems with blood flow.
A clot or other obstruction can make it difficult to achieve the prescribed dialysis blood flow.
Sometimes the catheter needs medical treatment, repositioning, replacement, or another intervention.
Central Vein Problems
Long-term use of a central venous catheter can contribute to central venous narrowing or stenosis in some patients.
This can become particularly important if the patient later needs an AV fistula or graft.
For this reason, preserving central veins is an important part of long-term vascular access planning.
KDOQI materials specifically include guidance on central venous catheter complications, including catheter dysfunction and catheter-related infection.
Is an AV Fistula Completely Risk-Free?
No.
Although an AV fistula is generally preferred for suitable patients, it is not completely free from complications.
Possible problems include:
- Failure to mature: The fistula may not develop enough blood flow or size to be used effectively for dialysis.
- Narrowing or stenosis: A narrowed section can reduce blood flow through the access.
- Thrombosis: A blood clot can block the fistula.
- Aneurysmal changes: Repeated needle use and changes in the vessel wall can sometimes cause enlargement of parts of the access.
- Hand circulation problems: In some patients, the increased blood flow through the fistula can contribute to reduced blood flow to the hand, a condition sometimes called steal syndrome.
- Infection: Although less common than with catheters, infection can still occur.
The access should therefore be monitored regularly rather than assuming that a fistula will always function perfectly.
How Do I Know My Fistula Is Working?
Patients can learn to check their fistula regularly.
A functioning fistula often produces a vibration or buzzing sensation called a thrill.
A healthcare professional can also listen to the access using a stethoscope to hear the characteristic blood-flow sound, called a bruit.
Patients should become familiar with how their access normally feels.
If the thrill suddenly disappears or changes significantly, the dialysis team should be contacted promptly.
The National Kidney Foundation recommends checking the access and reporting changes because problems with blood flow can sometimes require urgent attention.
How Should an AV Fistula Be Protected?
Once a fistula has been created, protecting the access becomes an important part of daily life.
Patients should tell healthcare professionals that they have dialysis access.
Some important precautions include:
- Avoid blood pressure measurements on the fistula arm unless specifically advised otherwise by the kidney-care team.
- Avoid unnecessary blood draws and IV lines from the fistula arm whenever possible. Preserving veins is important for current and future vascular access.
- Check the fistula regularly for its usual thrill or vibration. Any sudden change should be reported promptly.
- Keep the access clean and follow dialysis-team instructions for skin care.
- Avoid pressure or tight clothing over the access. Your healthcare team can provide specific advice about safe activities.
How Should a Dialysis Catheter Be Protected?
Catheter care is equally important.
Because the catheter provides direct access to the bloodstream, infection prevention is extremely important.
Patients should follow the dialysis team’s instructions regarding catheter dressing, bathing, and keeping the catheter site clean and dry.
The catheter should not be manipulated unnecessarily.
If the dressing becomes loose, wet, dirty, or damaged, the dialysis team should be contacted according to the center’s instructions.
Patients should also report symptoms such as:
- Fever or chills.
- Redness around the catheter site.
- Swelling or increasing pain.
- Drainage from the catheter site.
- Unexplained weakness or feeling acutely unwell.
- Problems with catheter blood flow during dialysis.
Early recognition of infection or access dysfunction can help prevent more serious complications.
Can a Patient Start With a Catheter and Later Get a Fistula?
Yes.
This is a common situation.
A patient may need dialysis urgently and therefore receive a catheter first.
At the same time, the kidney-care team may evaluate the patient’s blood vessels and plan an AV fistula if long-term hemodialysis is expected.
Once the fistula has matured and is functioning adequately, the catheter may no longer be necessary.
This approach allows dialysis to begin when needed while giving the permanent access time to develop.
The goal is not necessarily to avoid every catheter under every circumstance. The goal is to use the most appropriate access for the patient’s current needs and long-term kidney-care plan.
What Is an AV Graft?
An AV graft is another type of hemodialysis access.
It uses a soft synthetic tube to connect an artery and vein.
A graft may be considered when a patient’s veins are not suitable for creating a native AV fistula.
It can be useful for patients who need permanent access but do not have suitable anatomy for a fistula.
However, compared with a fistula, grafts generally have a greater risk of infection and clotting and may require more interventions to keep them working.
The choice between fistula, graft, and catheter should therefore be individualized.
Catheter vs Fistula: A Simple Comparison
Feature | AV Fistula | Dialysis Catheter |
Location | Usually arm | Usually neck/chest |
How it is created | Artery connected to nearby vein | Tube inserted into a large vein |
Can it be used immediately? | Usually no; needs maturation | Generally yes after appropriate placement |
Infection risk | Generally lower | Generally higher |
Long-term suitability | Generally preferred when feasible | Usually used for temporary access |
Needles during dialysis | Yes | No dialysis needles into the access |
Long-term suitability | Generally preferred when feasible | Usually used for temporary access |
Planning required | Yes | Less planning for urgent dialysis |
Suitable for emergency dialysis | Usually not immediately | Yes |
Alternative | Graft if fistula unsuitable | May remain necessary if permanent access is not possible |
This comparison is a general guide. The best access for an individual patient depends on their blood vessels, expected dialysis duration, medical condition, treatment plan, and overall health.
Why Vein Preservation Matters Before Dialysis
Patients with advanced CKD should think about their veins as an important resource.
Repeated blood draws, IV lines, and unnecessary procedures in the arms can damage veins that might later be needed for dialysis access.
This is why vein preservation can be important in patients who may eventually require hemodialysis.
Discuss with your kidney-care team which arm or veins should be protected.
If you already have an AV fistula, healthcare professionals should be informed so that the access arm can be protected appropriately.
When Should You Talk About a Fistula?
The right time depends on the individual’s kidney function, rate of CKD progression, overall health, vascular anatomy, and expected need for dialysis.
It is better to discuss vascular access before dialysis becomes an emergency.
If a patient waits until dialysis is urgently required, there may not be enough time for a fistula to mature.
In that situation, a catheter may be necessary.
Early planning gives the medical team more options and allows time for vascular mapping, surgical evaluation, fistula creation, and maturation when appropriate.
For anyone consulting a Kidney Specialist in Vijayawada, asking about future dialysis access can be particularly important when kidney function is progressively declining.
Is Fistula Always the Best Choice for Every Patient?
Not necessarily.
Although AV fistula is generally preferred when feasible, patient-centered planning is essential.
Some patients may have blood vessels that are too small or unsuitable for a fistula.
Some may have significant medical conditions that affect the choice of access.
Some patients may need dialysis only temporarily.
Others may have a short expected dialysis duration or may be approaching kidney transplantation.
In such cases, a catheter or graft may be more appropriate.
Current vascular-access guidance emphasizes choosing an access strategy that fits the patient’s individual kidney-failure treatment plan rather than applying one approach identically to every person.
What Should Patients Ask Before Getting Dialysis Access?
Before undergoing an access procedure, patients can ask their kidney-care team several useful questions.
- Do I need dialysis now, or is it likely that I will need dialysis in the future?
- Is my kidney disease temporary or permanent?
- Are my blood vessels suitable for an AV fistula?
- Which location would be best for my fistula?
- How long might my fistula take to mature?
- Should I see a vascular surgeon or vascular access specialist?
- What should I do to protect my veins before dialysis begins?
- What warning signs should make me contact the dialysis team?
These questions can help patients understand their choices instead of approaching dialysis access as something that simply happens to them.
Why Choosing the Right Vascular Access Matters
Dialysis access is sometimes called a patient’s lifeline because it is used repeatedly to deliver hemodialysis.
A patient who receives dialysis several times a week depends on that access for every treatment.
A well-functioning access can make dialysis more reliable and reduce avoidable complications.
However, maintaining the access requires cooperation between the patient, nephrologist, vascular surgeon, dialysis nurses, and other members of the healthcare team.
The patient also plays an important role by checking the access, following care instructions, protecting the access arm, and reporting changes early.
For people searching for a Kidney Specialist in Vijayawada, comprehensive care should include not only dialysis treatment but also appropriate vascular-access planning and long-term monitoring.
What Makes the American Kidney Institute’s Approach Important?
Dialysis access decisions should be made as part of an overall kidney-care plan.
At American Kidney Institute, patients can discuss their kidney condition, dialysis requirements, vascular access options, and long-term treatment needs with a nephrology team.
The choice of access depends on the individual patient’s condition rather than simply choosing the same option for everyone.
Patients who may require long-term hemodialysis can discuss whether an AV fistula is appropriate and whether enough time is available for it to mature.
Patients who need urgent dialysis can be assessed for appropriate immediate access while longer-term options are considered.
This individualized approach can help patients understand why a particular access has been recommended.
Final Takeaway: Catheter or AV Fistula?
So, which is better for dialysis: catheter or AV fistula?
For patients who need long-term hemodialysis and have suitable blood vessels, an AV fistula is generally the preferred option because it tends to have fewer infections and other complications and can provide durable vascular access.
A catheter, however, has an important role.
It can provide rapid access when dialysis must begin urgently. It may also be used while a fistula is maturing or when a fistula or graft cannot be created.
The important thing is not to think of the catheter as “wrong” and the fistula as “right” in every situation.
Instead, think about temporary access versus long-term access.
If your nephrologist expects that you may need long-term hemodialysis, discussing an AV fistula early can give enough time for evaluation, creation, and maturation.
If you have already started dialysis with a catheter, that does not necessarily mean you will always need the catheter. Depending on your condition, a fistula or graft may later become an option.
For patients searching for a Kidney Specialist in Vijayawada, early discussion about vascular access can help make dialysis planning safer and more organized.
At American Kidney Institute, patients can discuss their dialysis access options and understand which approach may be appropriate for their individual kidney-care plan.
The most important message is simple:
A catheter can be lifesaving when dialysis is needed urgently, while an AV fistula is generally preferred for long-term hemodialysis when it is suitable for the patient.
Frequently Asked Questions About Dialysis Catheter and AV Fistula
1. Which is better for dialysis, a catheter or AV fistula?
For patients who need long-term hemodialysis and have suitable blood vessels, an AV fistula is generally preferred.
It usually has a lower infection risk and better long-term durability than a dialysis catheter.
A catheter remains important when dialysis is needed urgently or when a fistula is not suitable.
2. Why is an AV fistula preferred over a catheter?
An AV fistula uses the patient’s own artery and vein and is located completely under the skin between dialysis treatments.
Compared with a catheter, it generally has fewer infections and can provide more durable access for long-term dialysis.
However, it needs time to mature before it can usually be used.
3. Can a dialysis catheter be used permanently?
A catheter is generally intended for short-term use, but it may sometimes be used longer when a fistula or graft cannot be created.
Long-term catheter use carries higher risks of infection, blockage, and other complications than a suitable permanent AV access.
The access plan should therefore be discussed individually with the nephrology team.
4. How long does an AV fistula take to mature?
An AV fistula needs time for the vein to enlarge and strengthen so that it can safely provide the required dialysis blood flow.
The maturation period varies from patient to patient, and some fistulas may need additional evaluation or intervention before they are usable.
Your nephrologist and vascular access team will determine when the fistula is ready for dialysis.
5. Can I get a fistula after starting dialysis with a catheter?
Yes, many patients start dialysis with a catheter and later transition to an AV fistula if long-term hemodialysis is expected.
The patient’s blood vessels are evaluated, and a fistula can be created if the anatomy and overall health are suitable.
The catheter may be removed once the permanent access is mature and functioning adequately.