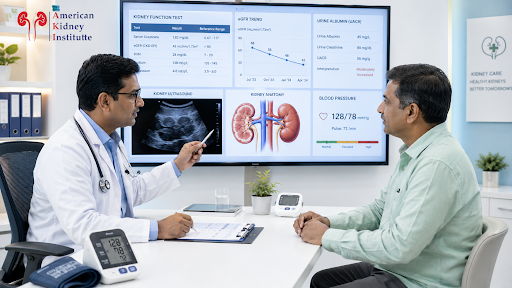
Kidney Specialist in Vijayawada: What to Expect at Your First Consultation

Kidney Specialist in Vijayawada: What to Expect at Your First Consultation A kidney specialist in Vijayawada is a nephrologist. A nephrologist is a doctor trained to diagnose and treat kidney diseases, including: Chronic kidney disease (CKD) High creatinine Protein in urine Kidney damage due to diabetes or high blood pressure Dialysis and kidney transplant care At your first visit, expect a review of your medical history and medicines, blood tests (creatinine, eGFR), urine tests (urine albumin), and a kidney ultrasound if needed. Experienced kidney specialists are available at American Kidney Institute, Vijayawada, with laboratory and imaging services in the same hospital Introduction Many patients reach a kidney specialist only after a routine blood test shows a “high creatinine” value, or after a family doctor says, “Please show this to a kidney doctor.” Then the questions start: When should I see a kidney specialist? What will they check? What do these numbers on my report mean? This guide answers those questions in simple language, so you walk into your consultation prepared and walk out with a clear plan. What Does a Kidney Specialist Do? Your kidneys do several important jobs: Filter waste and extra water from the blood Balance salts like sodium and potassium Help control blood pressure Support red blood cell production and bone health When any of these jobs are affected, a kidney specialist (nephrologist) steps in. A kidney specialist typically: Finds out why kidney function is falling, not just how much Slows down the progression of chronic kidney disease Manages kidney problems linked to diabetes and high blood pressure Treats protein leakage in urine, swelling, and electrolyte imbalances Adjusts medicines that may be harmful to weak kidneys Plans and supervises dialysis when it becomes necessary Prepares patients for a kidney transplant and cares for them afterwards Is a Urologist Also a Kidney Specialist? Not exactly. A kidney specialist is a nephrologist, who treats how well the kidneys work using medicines, diet guidance, and dialysis when needed. A urologist is a surgeon who treats physical problems in the urinary tract, such as kidney stones and blockages. If a structural problem like a stone is found, your nephrologist may refer you to a urologist. At American Kidney Institute, urology support is available in the same hospital, so referrals are quick. Who Should See a Kidney Specialist? You should consider booking a consultation if: Your blood test shows raised creatinine or a low eGFR Your urine test shows protein or albumin You have had diabetes or high blood pressure for several years and have never had your kidneys checked Someone in your family has kidney disease or is on dialysis Your family doctor or diabetologist has referred you You take painkillers regularly, or other medicines that may affect the kidneys You have had kidney stones more than once and want to protect your kidney function Kidney disease is often silent in its early stages. Many people feel completely normal while their kidney function is already reduced. Testing, not symptoms, is what catches it early. How to Prepare for Your First Visit A well-prepared visit gives the doctor a clearer picture and avoids repeating tests unnecessarily. Bring these with you: All old reports, especially previous creatinine values. The trend over months or years matters more than one single number. A list of all medicines, including painkillers, supplements, ayurvedic or herbal products, and over-the-counter tablets. Previous scan reports (ultrasound, CT) and discharge summaries, if any. Your BP and sugar readings, if you check them at home. Family history of kidney disease, diabetes, or dialysis. Write down your questions beforehand. For example: What is the cause of my kidney problem? What stage is my kidney function at? Do I need to change any of my current medicines? What should I eat and avoid? How often should I repeat my tests? What Happens During the Consultation? 1. Medical History and Examination The doctor will ask about your symptoms, past illnesses, medicines, and lifestyle. They will check your blood pressure, look for swelling, and examine you. 2. Blood Tests Serum creatinine: A waste product filtered by the kidneys. Higher levels can mean the kidneys are not filtering well. eGFR (estimated Glomerular Filtration Rate): Calculated from creatinine, age, and sex. It gives an estimate of how well your kidneys are filtering. Other blood tests: Blood urea, electrolytes (sodium, potassium), haemoglobin, calcium, and phosphorus show how kidney problems are affecting the rest of the body. 3. Urine Tests Urine routine examination: Checks for protein, blood, pus cells, and sugar. Urine albumin-to-creatinine ratio (UACR): One of the earliest signs of kidney damage, especially in people with diabetes. 4. Imaging A kidney ultrasound checks the size and shape of the kidneys, and looks for stones, cysts, or blockage. A CT scan may be advised in some cases. 5. Kidney Biopsy (Only in Selected Cases) If the cause is unclear, especially with heavy protein or blood in urine, the kidney specialist may suggest taking a small tissue sample to find the exact disease. Most patients do not need this. How to Read Your Kidney Report: A Simple Guide Your eGFR number helps the kidney specialist decide your CKD stage: eGFR (mL/min/1.73m²) Stage What It Generally Means 90 or above G1 Normal filtering; kidney damage may still be present if urine shows protein 60–89 G2 Mildly reduced 45–59 G3a Mild to moderately reduced 30–44 G3b Moderately to severely reduced 15–29 G4 Severely reduced; planning for future treatment begins Below 15 G5 Kidney failure; dialysis or transplant may be needed Important points to remember: One abnormal result is not a diagnosis. Chronic kidney disease is confirmed when changes last for more than three months. Dehydration, a recent illness, or certain medicines can temporarily affect results. Creatinine ranges vary by laboratory, age, sex, and muscle mass. Always read your value against the range printed on your report, and let your kidney specialist interpret it. Protein in urine matters even if eGFR is normal. It can be an early warning sign that needs treatment.
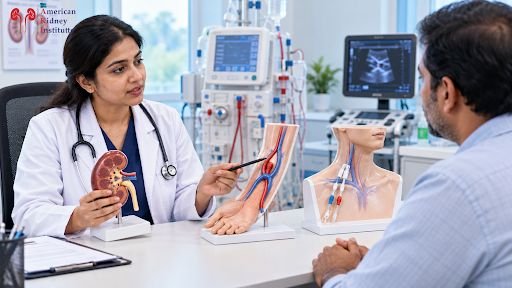
Which Is Better for Dialysis: Catheter or AV Fistula? A Complete Guide

Which Is Better for Dialysis: Catheter or AV Fistula? A Complete Guide Starting hemodialysis is a major change in a patient’s life. Along with understanding the dialysis process, one of the most important decisions is choosing the right vascular access. Vascular access is the route through which blood leaves the body, travels to the dialysis machine for cleaning, and returns to the bloodstream. Without reliable vascular access, hemodialysis cannot be performed effectively. The two options patients commonly hear about are a dialysis catheter and an AV fistula. Although both can provide access for hemodialysis, they are very different in how they are created, how quickly they can be used, and the risks associated with them. For many patients who are expected to need long-term hemodialysis, an AV fistula is generally preferred because it usually has fewer complications and better long-term durability than a central venous catheter. However, a catheter can be extremely useful when dialysis needs to begin urgently or when a fistula or graft is not suitable. For patients looking for a Kidney Specialist in Vijayawada, understanding these differences can make conversations about dialysis planning much easier. What Is Vascular Access for Hemodialysis? During hemodialysis, blood needs to move from the patient’s body to a dialysis machine. The machine passes the blood through a special filter called a dialyzer, where waste products and excess fluid are removed. The cleaned blood is then returned to the body. A vascular access provides this connection between the patient’s bloodstream and the dialysis machine. There are three major types of hemodialysis vascular access: AV fistula: A surgeon connects an artery and a nearby vein, usually in the arm, creating a stronger blood vessel that can later be used for dialysis needles. AV graft: A special tube is used to connect an artery and vein when the patient’s own blood vessels are not suitable for a fistula. Dialysis catheter: A soft tube is placed into a large vein, commonly in the neck or chest, allowing blood to be taken from and returned to the body without placing needles into an AV access. Each option has a role, but they are not interchangeable in every situation. What Is an AV Fistula? An arteriovenous fistula, commonly called an AV fistula or simply a fistula, is a surgically created connection between an artery and a nearby vein. It is usually created in the arm. The connection allows arterial blood flow to enter the vein, causing the vein to become larger and stronger over time. Once the fistula has matured sufficiently, dialysis needles can be placed into it during hemodialysis. An AV fistula uses the patient’s own blood vessels rather than an artificial tube. This is one of the major reasons it is generally preferred for long-term hemodialysis when it is medically suitable. The National Kidney Foundation describes a fistula as the preferred access because it generally has fewer problems and lasts longer than other access types. What Is a Dialysis Catheter? A dialysis catheter is a soft, flexible tube placed into a large vein. For hemodialysis, the catheter is commonly placed in a large vein in the neck, although other sites may be considered depending on the patient’s circumstances. Unlike a fistula, the catheter does not require the patient to wait for the access to mature before it can be used. This makes it particularly useful when dialysis needs to start urgently. For example, a patient who develops severe acute kidney injury and suddenly requires dialysis may not have enough time to wait for a fistula to mature. In such situations, a catheter may provide immediate access. However, because the catheter enters a large vein and has an external component, it carries higher risks of infection and other access-related complications than a well-functioning AV fistula. AV Fistula vs Dialysis Catheter: Which Is Better? For a patient who needs long-term hemodialysis and has suitable blood vessels, an AV fistula is generally preferred over a dialysis catheter. This does not mean that a catheter is a “bad” option. A catheter can be the right option in an emergency, during the period before a fistula is ready, or when an AV fistula or graft cannot be created. The difference is mainly about the intended duration, patient’s condition, vascular anatomy, and urgency of dialysis. A fistula generally offers better long-term durability and a lower risk of infection than a catheter. A catheter, on the other hand, provides rapid access and does not require maturation. Why Is an AV Fistula Preferred for Long-Term Dialysis? There are several reasons why an AV fistula is generally preferred when it is appropriate for the patient. Lower Infection Risk One of the major advantages of a fistula is the lower risk of bloodstream infection compared with a dialysis catheter. A catheter creates a direct pathway through the skin into a large vein. Because part of the catheter remains outside the body, strict infection-control practices are essential. A mature fistula is completely under the skin between dialysis sessions. This does not mean that a fistula can never become infected, but its infection risk is generally lower than that of a central venous catheter. Better Long-Term Durability An appropriately functioning AV fistula can provide vascular access for a long period. Because it is created using the patient’s own blood vessels, it does not depend on a synthetic tube or an external catheter. However, fistulas can develop problems such as narrowing, clotting, aneurysmal changes, or failure to mature. Regular monitoring helps identify these issues early. Good Blood Flow A mature fistula is designed to provide the blood flow needed for hemodialysis. During dialysis, two needles are typically placed into the fistula. One needle allows blood to travel toward the dialysis machine, while the other returns the cleaned blood to the patient. Good blood flow is important for delivering an effective dialysis treatment. Why Is a Dialysis Catheter Used? Although fistulas are generally preferred for long-term access, dialysis catheters remain very important. The biggest advantage is immediate usability. A

Does Starting Dialysis Mean You Need It for Life? AKI vs CKD Explained

Does Starting Dialysis Mean You Need It for Life? AKI vs CKD Explained Starting dialysis can be frightening for both patients and their families. One of the first questions many people ask is, “Once dialysis starts, will I have to continue it for the rest of my life?” The answer is not always. Whether dialysis is temporary or long-term depends mainly on why the kidneys stopped working and whether the kidney damage can recover. Acute Kidney Injury (AKI) and Chronic Kidney Disease (CKD) are two very different conditions, and the need for dialysis can be very different in each. In some patients with AKI, dialysis may be needed only for a few days or weeks while the kidneys recover. In advanced CKD, however, the kidneys may have permanent damage, and long-term dialysis or kidney transplantation may become necessary. For anyone searching for the Best Nephrologist in Vijayawada, understanding the difference between AKI and CKD is an important first step in understanding why dialysis has been recommended. What Is Dialysis? Dialysis is a treatment that performs some of the important functions normally carried out by healthy kidneys. Healthy kidneys remove waste products and excess fluid from the blood. They also help maintain the body’s electrolyte and acid-base balance. When kidney function becomes severely reduced, waste products, excess fluid, potassium, and acids can build up in the body. Dialysis helps remove these substances when the kidneys are unable to do so adequately. There are two main types of dialysis: Hemodialysis: Blood is passed through a special filter called a dialyzer, where waste products and excess fluid are removed before the blood is returned to the body. Peritoneal dialysis: The patient’s peritoneum, which is the lining inside the abdomen, is used as a natural filtering membrane with the help of dialysis fluid. The type of dialysis depends on the patient’s medical condition, kidney function, lifestyle, treatment needs, and medical advice. When patients search for Dialysis in Vijayawada, they should understand that dialysis is not a single treatment plan that is identical for every patient. The duration and frequency depend on the underlying kidney condition. Does Starting Dialysis Mean It Will Continue for Life? No. Starting dialysis does not automatically mean that dialysis will be lifelong. This is one of the most important things patients should understand. The kidneys can sometimes recover after a sudden injury. If dialysis was started because of an episode of AKI, the treatment may be temporary. For example, severe infection, dehydration, very low blood pressure, certain medicines, or other medical problems can suddenly affect kidney function. If the underlying problem is treated and the kidneys recover, dialysis may eventually be stopped. On the other hand, advanced CKD usually develops over many years. When a large amount of kidney tissue has been permanently damaged, the kidneys may not recover enough to perform their essential functions independently. In such situations, long-term dialysis or kidney transplantation may be required. Therefore, the most important question is not simply “Have I started dialysis?” The more important question is: “Why did my kidneys stop working?” What Is Acute Kidney Injury? Acute Kidney Injury, commonly called AKI, is a sudden decrease in kidney function. It can develop within hours or days. Unlike CKD, AKI may be reversible, depending on the cause and severity of the injury. Some patients with severe AKI may temporarily need dialysis because their kidneys cannot remove enough waste and fluid from the body. However, once the underlying cause is treated and kidney function improves, dialysis may no longer be necessary. This is why patients with AKI should not immediately assume that dialysis will continue permanently. Common Causes of Acute Kidney Injury AKI can occur for many different reasons. Some of the common causes include: Severe infections such as sepsis: A serious infection can cause low blood pressure, inflammation, and reduced blood flow to the kidneys, leading to sudden kidney injury. Severe dehydration: Significant loss of fluids due to vomiting, diarrhea, excessive sweating, poor fluid intake, or other causes can reduce blood flow to the kidneys. Very low blood pressure: Conditions such as severe infection, major blood loss, or shock can reduce the blood supply reaching the kidneys. Certain medicines or toxins: Some medicines can injure the kidneys, especially when used inappropriately or in vulnerable patients. Urinary obstruction: Problems that block the normal flow of urine can sometimes cause kidney function to deteriorate. Inflammatory or immune-related kidney diseases: Certain conditions can directly affect kidney tissue and cause sudden deterioration in kidney function. The treatment of AKI focuses on identifying and correcting the underlying cause while supporting the patient until the kidneys recover. When Is Dialysis Needed in AKI? Not every patient with AKI requires dialysis. Doctors decide whether dialysis is necessary based on the patient’s overall condition rather than one blood test alone. Dialysis may be considered when kidney failure leads to problems that cannot be safely managed with medicines and supportive treatment. Some important situations include: Severe fluid overload: When the kidneys cannot remove excess fluid and the patient develops serious fluid accumulation, dialysis may be needed to remove the extra fluid. Dangerously high potassium levels: Severe hyperkalemia can affect the heart and may require urgent treatment, including dialysis in selected situations. Severe metabolic acidosis: When the body becomes excessively acidic and the problem cannot be adequately corrected with medical treatment, dialysis may be considered. Significant accumulation of waste products: Severe buildup of waste products can cause symptoms and complications that may require dialysis. Certain severe complications of kidney failure: The patient’s symptoms and overall clinical condition may make dialysis necessary. In these situations, dialysis acts as supportive treatment while doctors work to treat the cause of AKI. Can Dialysis Be Stopped After AKI? Yes, dialysis can sometimes be stopped when kidney function recovers sufficiently. This is one of the biggest differences between temporary dialysis for AKI and maintenance dialysis for advanced CKD. When a patient is receiving dialysis for AKI, the nephrology team regularly monitors kidney function and the patient’s

Kidney Biopsy for Glomerulonephritis, AKI, CKD, and Transplant Rejection

Kidney Biopsy for Glomerulonephritis, AKI, CKD, and Transplant Rejection Kidney diseases do not always show their exact cause through routine blood and urine tests. Tests such as serum creatinine, eGFR, urine protein, and urine analysis can tell us that the kidneys are not functioning normally. However, in some patients, these tests cannot tell us exactly what is happening inside the kidney. This is where a kidney biopsy can become important. A kidney biopsy is a diagnostic procedure in which a very small piece of kidney tissue is removed and examined under a microscope. The tissue can provide detailed information about the type of kidney disease, the pattern of kidney injury, inflammation, scarring, and other changes that may not be visible through routine tests. A kidney biopsy may be recommended in conditions such as glomerulonephritis, unexplained acute kidney injury (AKI), chronic kidney disease (CKD) of unknown cause, significant protein in the urine, and suspected rejection after a kidney transplant. The information obtained from a biopsy can help the nephrologist understand the disease more accurately and select an appropriate treatment plan. For patients looking for specialized kidney care, choosing a Best Kidney Hospital in Vijayawada can provide access to nephrology evaluation, diagnostic testing, biopsy services, and appropriate follow-up care under specialist supervision. What Is a Kidney Biopsy? A kidney biopsy is a procedure used to obtain a small sample of kidney tissue for detailed laboratory examination. Although blood and urine tests are extremely useful, they mainly provide information about kidney function and the substances being removed or retained by the kidneys. A biopsy can provide a much closer look at the kidney tissue itself. The sample is usually examined using different laboratory techniques. These may include routine microscopic examination, immunological staining, and electron microscopy when required. These examinations can help identify specific patterns of kidney injury. For example, two patients may both have high serum creatinine and protein in their urine, but the underlying diseases may be completely different. One patient may have an immune-related kidney disease, while another may have a different type of glomerular injury. The treatment for these conditions may also be different. Therefore, understanding the exact kidney disease can be important before starting certain treatments. Why Is a Kidney Biopsy Needed? A kidney biopsy is not required for every person with kidney disease. The decision is usually based on the patient’s symptoms, blood test results, urine findings, imaging results, medical history, and the suspected kidney condition. A nephrologist may recommend a biopsy when knowing the exact cause of kidney damage is likely to change the treatment or help determine the expected outcome. A biopsy may help answer important questions such as: What type of kidney disease is causing the abnormal kidney function? A biopsy can help identify specific patterns of kidney injury that cannot always be distinguished through blood and urine tests alone. Is the kidney injury caused by inflammation, an immune reaction, infection, medication, or another process? Identifying the pattern of injury can help doctors understand the underlying disease. How much active damage and permanent scarring are present? This information may help doctors assess the possibility of recovery and guide treatment decisions. Would immunosuppressive treatment be appropriate? In selected kidney diseases, biopsy findings can help determine whether medicines that suppress abnormal immune activity may be useful. Is a transplanted kidney showing signs of rejection? In transplant patients, biopsy can help determine the cause of worsening kidney function when rejection is suspected. For people seeking a Best Kidney Hospital in Vijayawada, it is important to choose a center where kidney biopsy findings are interpreted along with the patient’s clinical history, blood tests, urine tests, and imaging. Kidney Biopsy for Glomerulonephritis Glomerulonephritis refers to inflammation or other injury involving the glomeruli, which are tiny filtering structures inside the kidneys. The glomeruli play an important role in filtering blood. When they become damaged, proteins or blood cells may leak into the urine, and kidney function may gradually or suddenly decrease. Patients with glomerulonephritis may experience symptoms such as blood in the urine, swelling, high blood pressure, increased protein in the urine, or reduced kidney function. However, glomerulonephritis is not a single disease. There are different types and patterns of glomerular disease. The treatment can vary significantly depending on the underlying cause. A kidney biopsy can help distinguish between these patterns. What Can the Biopsy Show in Glomerulonephritis? A biopsy may show inflammation, immune deposits, changes in the glomeruli, scarring, or other structural abnormalities. The findings can help the nephrologist classify the kidney disease and understand whether the damage appears to be active, chronic, or a combination of both. This distinction can be important because active inflammation may sometimes respond to appropriate treatment, while extensive permanent scarring may indicate a lower likelihood of complete recovery. Why Does Accurate Diagnosis Matter? Treatment for glomerulonephritis depends on its underlying cause. Some patients may require medicines to control blood pressure and reduce protein loss. Others may require treatment directed at an abnormal immune response. In certain cases, treatment may focus on an underlying infection or another medical condition. A biopsy can provide valuable evidence when the diagnosis is uncertain or when treatment decisions depend on identifying the exact type of kidney disease. Kidney Biopsy for Acute Kidney Injury (AKI) Acute kidney injury means that kidney function has decreased over a short period of time. AKI can happen for many reasons. Dehydration, severe infection, low blood pressure, certain medicines, urinary obstruction, autoimmune diseases, and direct injury to kidney tissue are among the possible causes. In many patients, doctors can identify the likely cause of AKI through history, examination, blood tests, urine tests, and imaging. However, sometimes kidney function does not improve as expected. When AKI continues without a clear explanation, a kidney biopsy may be considered. When Can Biopsy Be Considered in AKI? A biopsy may be useful when: Kidney function continues to worsen or does not recover despite appropriate initial treatment. This can indicate that the underlying cause needs further investigation. Routine investigations

How Nephrologists Diagnose and Treat Chronic Kidney Disease

How Nephrologists Diagnose and Treat Chronic Kidney Disease Chronic kidney disease, commonly called CKD, is a long-term condition in which the kidneys become damaged or their ability to filter blood decreases over time. The condition can affect people of different ages and may develop because of diabetes, high blood pressure, inherited kidney disorders, autoimmune diseases, repeated kidney injury, and other medical conditions. One of the biggest challenges with CKD is that it can develop quietly. Many people do not experience clear symptoms during the early stages. Blood and urine tests may identify kidney damage before a person feels unwell. This is where a nephrologist plays an important role. A nephrologist is a doctor who specializes in kidney diseases. Nephrologists do more than treat advanced kidney failure. They investigate why kidney function is changing, assess the severity of kidney disease, manage complications, and create treatment plans designed to protect remaining kidney function. For people searching for the Best Nephrologist in Vijayawada, understanding how CKD is diagnosed and treated can help them recognize the importance of timely kidney care. What Is Chronic Kidney Disease? Chronic kidney disease means there is an abnormality in kidney structure or function that persists for at least three months. Healthy kidneys continuously filter the blood. They remove waste products and excess fluid through urine while helping regulate electrolytes, acid-base balance, blood pressure, and other important body functions. When kidney function becomes reduced, waste products and excess substances may gradually accumulate in the body. CKD can also lead to complications involving blood pressure, anemia, bones, minerals, heart health, and nutrition. The condition does not always progress quickly. Some people remain stable for many years, while others experience a faster decline in kidney function. This difference makes regular monitoring important. Why Can Chronic Kidney Disease Go Unnoticed? Early CKD often does not produce obvious symptoms. A person may have an abnormal kidney test while continuing to work, eat, exercise, and carry out normal daily activities. Symptoms may become more noticeable as kidney function declines. These can include swelling, tiredness, nausea, poor appetite, changes in urination, itching, muscle cramps, or shortness of breath. However, symptoms alone cannot determine whether someone has CKD. Testing is important because blood and urine tests can identify kidney damage or reduced filtration before serious symptoms develop. Who Is at Higher Risk of CKD? Certain health conditions increase the risk of developing kidney disease. People who may need regular kidney evaluation include those with: Diabetes, particularly when blood glucose has been difficult to control over time. High blood pressure, especially when it remains uncontrolled or requires multiple medicines. Heart disease or other cardiovascular conditions associated with increased kidney risk. A family history of kidney failure or certain inherited kidney diseases. Previous episodes of acute kidney injury or repeated kidney-related problems. Conditions such as autoimmune diseases that can affect the kidney’s filtering structures. NIDDK identifies diabetes, hypertension, cardiovascular disease, and family history of kidney failure among important CKD risk factors. When Should You See a Nephrologist? You may need nephrology evaluation when kidney tests are repeatedly abnormal or when kidney function is changing. Common reasons include: Persistently elevated creatinine or reduced eGFR on blood tests. Protein or albumin repeatedly detected in urine. A rapid or unexplained decline in kidney function. Blood in the urine with other kidney abnormalities. High blood pressure that remains difficult to control. Unexplained swelling or fluid retention. Repeated kidney stones, infections, or other kidney-related problems. Abnormal potassium, calcium, phosphorus, or bicarbonate levels associated with reduced kidney function. Advanced CKD where dialysis or kidney transplantation may eventually need to be considered. Early specialist evaluation does not mean dialysis is immediately required. In many cases, the purpose is to understand the problem early and protect kidney function. How Do Nephrologists Diagnose CKD? Diagnosing CKD involves several pieces of information. A nephrologist may review your medical history, symptoms, previous laboratory reports, medications, blood pressure readings, blood tests, urine tests, and imaging results. The two major markers used to identify and monitor CKD are eGFR and urine albumin. The doctor also needs to determine whether the abnormality is truly chronic. An abnormal test caused by temporary dehydration or an acute illness should not automatically be labeled as chronic kidney disease. Understanding Creatinine Creatinine is a waste product produced through normal muscle metabolism. Healthy kidneys remove creatinine from the blood. When kidney filtration decreases, blood creatinine may increase. However, creatinine is not a perfect measure of kidney function by itself. Muscle mass, age, diet, certain medicines, and other factors can affect creatinine levels. For this reason, nephrologists usually interpret creatinine alongside eGFR and other findings. A single elevated creatinine result does not automatically mean that someone has permanent CKD. What Is eGFR? The estimated glomerular filtration rate, or eGFR, estimates how efficiently the kidneys filter blood. It is calculated using blood-test information and an established estimation equation. A persistently reduced eGFR can indicate chronic kidney disease. NIDDK notes that an eGFR below 60 may indicate kidney disease, while an eGFR of 15 or lower is generally considered the kidney failure range. However, doctors do not make treatment decisions based on eGFR alone. The patient’s symptoms, urine albumin, underlying cause, rate of change, other laboratory findings, age, and overall health also matter. Why Is Urine Testing Important? Blood tests tell doctors about kidney filtration, but urine tests provide different information. One important test is the urine albumin-to-creatinine ratio, or UACR. Albumin is a protein normally found in the blood. Healthy kidneys generally prevent significant amounts of albumin from passing into urine. When the kidney’s filtering barrier is damaged, albumin can leak into urine. Persistent albuminuria can therefore be an important sign of kidney damage. A UACR above 30 mg/g may indicate increased urine albumin, although results need to be interpreted in the clinical context and may be repeated for confirmation. What Other Urine Tests May Be Done? A nephrologist may order a complete urinalysis depending on the patient’s condition. The test can provide information about: Protein: Persistent protein

Translate »