Which Is Better for Dialysis: Catheter or AV Fistula? A Complete Guide

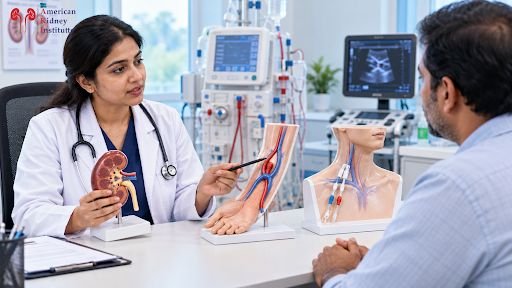
Which Is Better for Dialysis: Catheter or AV Fistula? A Complete Guide Starting hemodialysis is a major change in a patient’s life. Along with understanding the dialysis process, one of the most important decisions is choosing the right vascular access. Vascular access is the route through which blood leaves the body, travels to the dialysis machine for cleaning, and returns to the bloodstream. Without reliable vascular access, hemodialysis cannot be performed effectively. The two options patients commonly hear about are a dialysis catheter and an AV fistula. Although both can provide access for hemodialysis, they are very different in how they are created, how quickly they can be used, and the risks associated with them. For many patients who are expected to need long-term hemodialysis, an AV fistula is generally preferred because it usually has fewer complications and better long-term durability than a central venous catheter. However, a catheter can be extremely useful when dialysis needs to begin urgently or when a fistula or graft is not suitable. For patients looking for a Kidney Specialist in Vijayawada, understanding these differences can make conversations about dialysis planning much easier. What Is Vascular Access for Hemodialysis? During hemodialysis, blood needs to move from the patient’s body to a dialysis machine. The machine passes the blood through a special filter called a dialyzer, where waste products and excess fluid are removed. The cleaned blood is then returned to the body. A vascular access provides this connection between the patient’s bloodstream and the dialysis machine. There are three major types of hemodialysis vascular access: AV fistula: A surgeon connects an artery and a nearby vein, usually in the arm, creating a stronger blood vessel that can later be used for dialysis needles. AV graft: A special tube is used to connect an artery and vein when the patient’s own blood vessels are not suitable for a fistula. Dialysis catheter: A soft tube is placed into a large vein, commonly in the neck or chest, allowing blood to be taken from and returned to the body without placing needles into an AV access. Each option has a role, but they are not interchangeable in every situation. What Is an AV Fistula? An arteriovenous fistula, commonly called an AV fistula or simply a fistula, is a surgically created connection between an artery and a nearby vein. It is usually created in the arm. The connection allows arterial blood flow to enter the vein, causing the vein to become larger and stronger over time. Once the fistula has matured sufficiently, dialysis needles can be placed into it during hemodialysis. An AV fistula uses the patient’s own blood vessels rather than an artificial tube. This is one of the major reasons it is generally preferred for long-term hemodialysis when it is medically suitable. The National Kidney Foundation describes a fistula as the preferred access because it generally has fewer problems and lasts longer than other access types. What Is a Dialysis Catheter? A dialysis catheter is a soft, flexible tube placed into a large vein. For hemodialysis, the catheter is commonly placed in a large vein in the neck, although other sites may be considered depending on the patient’s circumstances. Unlike a fistula, the catheter does not require the patient to wait for the access to mature before it can be used. This makes it particularly useful when dialysis needs to start urgently. For example, a patient who develops severe acute kidney injury and suddenly requires dialysis may not have enough time to wait for a fistula to mature. In such situations, a catheter may provide immediate access. However, because the catheter enters a large vein and has an external component, it carries higher risks of infection and other access-related complications than a well-functioning AV fistula. AV Fistula vs Dialysis Catheter: Which Is Better? For a patient who needs long-term hemodialysis and has suitable blood vessels, an AV fistula is generally preferred over a dialysis catheter. This does not mean that a catheter is a “bad” option. A catheter can be the right option in an emergency, during the period before a fistula is ready, or when an AV fistula or graft cannot be created. The difference is mainly about the intended duration, patient’s condition, vascular anatomy, and urgency of dialysis. A fistula generally offers better long-term durability and a lower risk of infection than a catheter. A catheter, on the other hand, provides rapid access and does not require maturation. Why Is an AV Fistula Preferred for Long-Term Dialysis? There are several reasons why an AV fistula is generally preferred when it is appropriate for the patient. Lower Infection Risk One of the major advantages of a fistula is the lower risk of bloodstream infection compared with a dialysis catheter. A catheter creates a direct pathway through the skin into a large vein. Because part of the catheter remains outside the body, strict infection-control practices are essential. A mature fistula is completely under the skin between dialysis sessions. This does not mean that a fistula can never become infected, but its infection risk is generally lower than that of a central venous catheter. Better Long-Term Durability An appropriately functioning AV fistula can provide vascular access for a long period. Because it is created using the patient’s own blood vessels, it does not depend on a synthetic tube or an external catheter. However, fistulas can develop problems such as narrowing, clotting, aneurysmal changes, or failure to mature. Regular monitoring helps identify these issues early. Good Blood Flow A mature fistula is designed to provide the blood flow needed for hemodialysis. During dialysis, two needles are typically placed into the fistula. One needle allows blood to travel toward the dialysis machine, while the other returns the cleaned blood to the patient. Good blood flow is important for delivering an effective dialysis treatment. Why Is a Dialysis Catheter Used? Although fistulas are generally preferred for long-term access, dialysis catheters remain very important. The biggest advantage is immediate usability. A

Does Starting Dialysis Mean You Need It for Life? AKI vs CKD Explained

Does Starting Dialysis Mean You Need It for Life? AKI vs CKD Explained Starting dialysis can be frightening for both patients and their families. One of the first questions many people ask is, “Once dialysis starts, will I have to continue it for the rest of my life?” The answer is not always. Whether dialysis is temporary or long-term depends mainly on why the kidneys stopped working and whether the kidney damage can recover. Acute Kidney Injury (AKI) and Chronic Kidney Disease (CKD) are two very different conditions, and the need for dialysis can be very different in each. In some patients with AKI, dialysis may be needed only for a few days or weeks while the kidneys recover. In advanced CKD, however, the kidneys may have permanent damage, and long-term dialysis or kidney transplantation may become necessary. For anyone searching for the Best Nephrologist in Vijayawada, understanding the difference between AKI and CKD is an important first step in understanding why dialysis has been recommended. What Is Dialysis? Dialysis is a treatment that performs some of the important functions normally carried out by healthy kidneys. Healthy kidneys remove waste products and excess fluid from the blood. They also help maintain the body’s electrolyte and acid-base balance. When kidney function becomes severely reduced, waste products, excess fluid, potassium, and acids can build up in the body. Dialysis helps remove these substances when the kidneys are unable to do so adequately. There are two main types of dialysis: Hemodialysis: Blood is passed through a special filter called a dialyzer, where waste products and excess fluid are removed before the blood is returned to the body. Peritoneal dialysis: The patient’s peritoneum, which is the lining inside the abdomen, is used as a natural filtering membrane with the help of dialysis fluid. The type of dialysis depends on the patient’s medical condition, kidney function, lifestyle, treatment needs, and medical advice. When patients search for Dialysis in Vijayawada, they should understand that dialysis is not a single treatment plan that is identical for every patient. The duration and frequency depend on the underlying kidney condition. Does Starting Dialysis Mean It Will Continue for Life? No. Starting dialysis does not automatically mean that dialysis will be lifelong. This is one of the most important things patients should understand. The kidneys can sometimes recover after a sudden injury. If dialysis was started because of an episode of AKI, the treatment may be temporary. For example, severe infection, dehydration, very low blood pressure, certain medicines, or other medical problems can suddenly affect kidney function. If the underlying problem is treated and the kidneys recover, dialysis may eventually be stopped. On the other hand, advanced CKD usually develops over many years. When a large amount of kidney tissue has been permanently damaged, the kidneys may not recover enough to perform their essential functions independently. In such situations, long-term dialysis or kidney transplantation may be required. Therefore, the most important question is not simply “Have I started dialysis?” The more important question is: “Why did my kidneys stop working?” What Is Acute Kidney Injury? Acute Kidney Injury, commonly called AKI, is a sudden decrease in kidney function. It can develop within hours or days. Unlike CKD, AKI may be reversible, depending on the cause and severity of the injury. Some patients with severe AKI may temporarily need dialysis because their kidneys cannot remove enough waste and fluid from the body. However, once the underlying cause is treated and kidney function improves, dialysis may no longer be necessary. This is why patients with AKI should not immediately assume that dialysis will continue permanently. Common Causes of Acute Kidney Injury AKI can occur for many different reasons. Some of the common causes include: Severe infections such as sepsis: A serious infection can cause low blood pressure, inflammation, and reduced blood flow to the kidneys, leading to sudden kidney injury. Severe dehydration: Significant loss of fluids due to vomiting, diarrhea, excessive sweating, poor fluid intake, or other causes can reduce blood flow to the kidneys. Very low blood pressure: Conditions such as severe infection, major blood loss, or shock can reduce the blood supply reaching the kidneys. Certain medicines or toxins: Some medicines can injure the kidneys, especially when used inappropriately or in vulnerable patients. Urinary obstruction: Problems that block the normal flow of urine can sometimes cause kidney function to deteriorate. Inflammatory or immune-related kidney diseases: Certain conditions can directly affect kidney tissue and cause sudden deterioration in kidney function. The treatment of AKI focuses on identifying and correcting the underlying cause while supporting the patient until the kidneys recover. When Is Dialysis Needed in AKI? Not every patient with AKI requires dialysis. Doctors decide whether dialysis is necessary based on the patient’s overall condition rather than one blood test alone. Dialysis may be considered when kidney failure leads to problems that cannot be safely managed with medicines and supportive treatment. Some important situations include: Severe fluid overload: When the kidneys cannot remove excess fluid and the patient develops serious fluid accumulation, dialysis may be needed to remove the extra fluid. Dangerously high potassium levels: Severe hyperkalemia can affect the heart and may require urgent treatment, including dialysis in selected situations. Severe metabolic acidosis: When the body becomes excessively acidic and the problem cannot be adequately corrected with medical treatment, dialysis may be considered. Significant accumulation of waste products: Severe buildup of waste products can cause symptoms and complications that may require dialysis. Certain severe complications of kidney failure: The patient’s symptoms and overall clinical condition may make dialysis necessary. In these situations, dialysis acts as supportive treatment while doctors work to treat the cause of AKI. Can Dialysis Be Stopped After AKI? Yes, dialysis can sometimes be stopped when kidney function recovers sufficiently. This is one of the biggest differences between temporary dialysis for AKI and maintenance dialysis for advanced CKD. When a patient is receiving dialysis for AKI, the nephrology team regularly monitors kidney function and the patient’s

Kidney Biopsy for Glomerulonephritis, AKI, CKD, and Transplant Rejection

Kidney Biopsy for Glomerulonephritis, AKI, CKD, and Transplant Rejection Kidney diseases do not always show their exact cause through routine blood and urine tests. Tests such as serum creatinine, eGFR, urine protein, and urine analysis can tell us that the kidneys are not functioning normally. However, in some patients, these tests cannot tell us exactly what is happening inside the kidney. This is where a kidney biopsy can become important. A kidney biopsy is a diagnostic procedure in which a very small piece of kidney tissue is removed and examined under a microscope. The tissue can provide detailed information about the type of kidney disease, the pattern of kidney injury, inflammation, scarring, and other changes that may not be visible through routine tests. A kidney biopsy may be recommended in conditions such as glomerulonephritis, unexplained acute kidney injury (AKI), chronic kidney disease (CKD) of unknown cause, significant protein in the urine, and suspected rejection after a kidney transplant. The information obtained from a biopsy can help the nephrologist understand the disease more accurately and select an appropriate treatment plan. For patients looking for specialized kidney care, choosing a Best Kidney Hospital in Vijayawada can provide access to nephrology evaluation, diagnostic testing, biopsy services, and appropriate follow-up care under specialist supervision. What Is a Kidney Biopsy? A kidney biopsy is a procedure used to obtain a small sample of kidney tissue for detailed laboratory examination. Although blood and urine tests are extremely useful, they mainly provide information about kidney function and the substances being removed or retained by the kidneys. A biopsy can provide a much closer look at the kidney tissue itself. The sample is usually examined using different laboratory techniques. These may include routine microscopic examination, immunological staining, and electron microscopy when required. These examinations can help identify specific patterns of kidney injury. For example, two patients may both have high serum creatinine and protein in their urine, but the underlying diseases may be completely different. One patient may have an immune-related kidney disease, while another may have a different type of glomerular injury. The treatment for these conditions may also be different. Therefore, understanding the exact kidney disease can be important before starting certain treatments. Why Is a Kidney Biopsy Needed? A kidney biopsy is not required for every person with kidney disease. The decision is usually based on the patient’s symptoms, blood test results, urine findings, imaging results, medical history, and the suspected kidney condition. A nephrologist may recommend a biopsy when knowing the exact cause of kidney damage is likely to change the treatment or help determine the expected outcome. A biopsy may help answer important questions such as: What type of kidney disease is causing the abnormal kidney function? A biopsy can help identify specific patterns of kidney injury that cannot always be distinguished through blood and urine tests alone. Is the kidney injury caused by inflammation, an immune reaction, infection, medication, or another process? Identifying the pattern of injury can help doctors understand the underlying disease. How much active damage and permanent scarring are present? This information may help doctors assess the possibility of recovery and guide treatment decisions. Would immunosuppressive treatment be appropriate? In selected kidney diseases, biopsy findings can help determine whether medicines that suppress abnormal immune activity may be useful. Is a transplanted kidney showing signs of rejection? In transplant patients, biopsy can help determine the cause of worsening kidney function when rejection is suspected. For people seeking a Best Kidney Hospital in Vijayawada, it is important to choose a center where kidney biopsy findings are interpreted along with the patient’s clinical history, blood tests, urine tests, and imaging. Kidney Biopsy for Glomerulonephritis Glomerulonephritis refers to inflammation or other injury involving the glomeruli, which are tiny filtering structures inside the kidneys. The glomeruli play an important role in filtering blood. When they become damaged, proteins or blood cells may leak into the urine, and kidney function may gradually or suddenly decrease. Patients with glomerulonephritis may experience symptoms such as blood in the urine, swelling, high blood pressure, increased protein in the urine, or reduced kidney function. However, glomerulonephritis is not a single disease. There are different types and patterns of glomerular disease. The treatment can vary significantly depending on the underlying cause. A kidney biopsy can help distinguish between these patterns. What Can the Biopsy Show in Glomerulonephritis? A biopsy may show inflammation, immune deposits, changes in the glomeruli, scarring, or other structural abnormalities. The findings can help the nephrologist classify the kidney disease and understand whether the damage appears to be active, chronic, or a combination of both. This distinction can be important because active inflammation may sometimes respond to appropriate treatment, while extensive permanent scarring may indicate a lower likelihood of complete recovery. Why Does Accurate Diagnosis Matter? Treatment for glomerulonephritis depends on its underlying cause. Some patients may require medicines to control blood pressure and reduce protein loss. Others may require treatment directed at an abnormal immune response. In certain cases, treatment may focus on an underlying infection or another medical condition. A biopsy can provide valuable evidence when the diagnosis is uncertain or when treatment decisions depend on identifying the exact type of kidney disease. Kidney Biopsy for Acute Kidney Injury (AKI) Acute kidney injury means that kidney function has decreased over a short period of time. AKI can happen for many reasons. Dehydration, severe infection, low blood pressure, certain medicines, urinary obstruction, autoimmune diseases, and direct injury to kidney tissue are among the possible causes. In many patients, doctors can identify the likely cause of AKI through history, examination, blood tests, urine tests, and imaging. However, sometimes kidney function does not improve as expected. When AKI continues without a clear explanation, a kidney biopsy may be considered. When Can Biopsy Be Considered in AKI? A biopsy may be useful when: Kidney function continues to worsen or does not recover despite appropriate initial treatment. This can indicate that the underlying cause needs further investigation. Routine investigations

Why Is Erythropoietin Low in Kidney Disease and How Is It Treated?

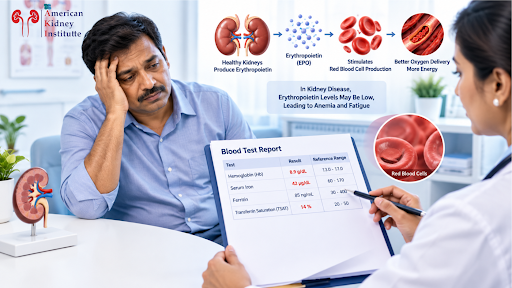
Why Is Erythropoietin Low in Kidney Disease and How Is It Treated? Feeling tired or weak is a common complaint among people living with kidney disease. Some patients may feel exhausted even after getting enough sleep, while others may notice weakness, reduced energy, poor concentration, or difficulty doing their usual daily activities. Many people may think that this tiredness is simply due to age, stress, lack of sleep, or the kidney disease itself. However, anemia is one of the important reasons for fatigue in people with chronic kidney disease. One of the major causes of anemia in kidney disease is a reduction in the production of a hormone called erythropoietin, also known as EPO. Healthy kidneys normally produce erythropoietin, which signals the bone marrow to make red blood cells. When kidney function decreases significantly, the kidneys may not produce enough erythropoietin. As a result, the bone marrow receives less stimulation to produce red blood cells, which can contribute to anemia. However, low erythropoietin is not the only reason kidney patients develop anemia. Iron deficiency, inflammation, blood loss, nutritional problems, and other medical conditions can also contribute. Understanding the connection between kidney disease, erythropoietin, hemoglobin, iron, and fatigue can help patients seek the right evaluation and treatment instead of simply accepting constant tiredness as a normal part of aging. What Is Erythropoietin? Erythropoietin is a hormone that plays an important role in red blood cell production. Most erythropoietin in adults is produced by specialized cells in the kidneys. When the body senses that tissues are not receiving enough oxygen, the kidneys normally increase erythropoietin production. Erythropoietin then travels through the bloodstream to the bone marrow. It stimulates the bone marrow to produce more red blood cells. Red blood cells contain hemoglobin, a protein that carries oxygen from the lungs to different parts of the body. Therefore, erythropoietin, red blood cells, hemoglobin, and oxygen delivery are closely connected. When kidney function becomes severely reduced, the kidneys may lose some of their ability to produce an adequate amount of erythropoietin. This can reduce red blood cell production and contribute to anemia. Why Does Erythropoietin Become Low in Kidney Disease? Healthy kidneys have several important functions, including filtering waste products, regulating fluid and electrolyte balance, and producing hormones. As chronic kidney disease progresses, damage to the kidney tissue can affect these functions. The cells responsible for producing erythropoietin can become less effective. Consequently, erythropoietin production may not increase adequately even when the body needs more red blood cells. This is one reason anemia becomes increasingly common as kidney disease advances. The relationship is not always simple. Some patients with kidney disease may have anemia even when erythropoietin levels are not extremely low because their bone marrow may not respond normally to erythropoietin. Inflammation, iron deficiency, infection, nutritional deficiencies, and blood loss can also interfere with healthy red blood cell production. Therefore, doctors do not usually diagnose the cause of anemia simply by looking at erythropoietin levels. A complete evaluation is needed. How Does Low Erythropoietin Cause Anemia? The process can be understood in a simple way. The kidneys produce erythropoietin, and erythropoietin tells the bone marrow to produce red blood cells. When kidney disease reduces this signal, the bone marrow may produce fewer red blood cells. With fewer red blood cells, the amount of oxygen carried to body tissues can decrease. This can result in symptoms such as tiredness, weakness, reduced stamina, dizziness, headaches, shortness of breath during activity, and difficulty concentrating. The severity of symptoms can vary considerably from one person to another. A patient with a mildly reduced hemoglobin level may have few symptoms, while another patient with more significant anemia may feel extremely tired and weak. Is Tiredness Always Due to Low Erythropoietin? No. This is an important point for kidney patients to understand. Fatigue can have many causes, and kidney disease itself can contribute to reduced energy. Anemia is one important cause, but it is not the only possible explanation. A patient may have iron deficiency, vitamin deficiencies, infection, inflammation, poor nutrition, sleep problems, heart disease, thyroid problems, medication-related effects, or other conditions that cause fatigue. For this reason, patients should not assume that every episode of tiredness means they need an erythropoietin injection. A doctor needs to identify the underlying cause before deciding on treatment. What Are the Common Symptoms of Anemia in Kidney Disease? Anemia can develop gradually, so some patients may not immediately recognize the symptoms. The body may adapt to a gradual reduction in red blood cells, and symptoms may become more noticeable as anemia becomes more severe. Common symptoms can include: Persistent tiredness and weakness that interfere with normal daily activities. A patient may feel exhausted after routine activities such as walking, climbing stairs, household work, or shopping. Shortness of breath, especially during physical activity. When oxygen delivery is reduced, the heart and lungs may need to work harder to meet the body’s oxygen requirements. Dizziness, headaches, or light-headedness. These symptoms can occur in some people with anemia, although they may also have other causes. Reduced concentration and difficulty feeling mentally alert. Some patients describe this as feeling mentally tired or unable to focus properly. Pale skin or pale appearance. Reduced hemoglobin can sometimes make the skin, lips, or inside of the eyelids appear paler than usual. Reduced exercise tolerance. Activities that were previously easy may become tiring, particularly when anemia becomes more significant. These symptoms should not automatically be attributed to kidney disease or age. Medical evaluation can help identify whether anemia or another condition is responsible. Understanding Chronic Kidney Disease Symptoms and Anemia Many patients search for Chronic Kidney Disease Symptoms when they begin experiencing fatigue, weakness, swelling, changes in urination, or other health problems. However, chronic kidney disease can sometimes progress without obvious symptoms during its early stages. As kidney function declines, symptoms may become more noticeable. Anemia is one of the complications that may develop as kidney disease progresses. Because fatigue has many possible causes, checking hemoglobin and iron-related blood

Why Should Dialysis Patients Control Water, Potassium and Phosphorus Intake?

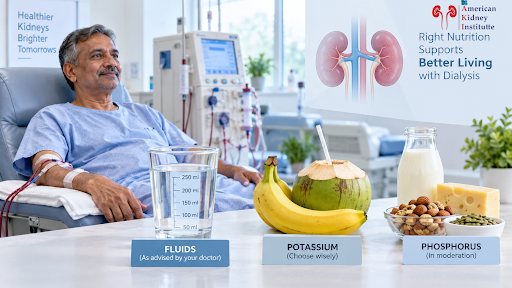
Why Should Dialysis Patients Control Water, Potassium and Phosphorus Intake? For people undergoing dialysis, food and fluid choices are an important part of everyday kidney care. When the kidneys are no longer able to remove enough waste and extra fluid from the body, substances such as water, sodium, potassium, and phosphorus can build up between dialysis sessions. Managing these levels can help reduce complications and support better overall health. Many dialysis patients have questions such as: How much water can I drink? Which foods contain too much potassium? Why should phosphorus be limited? Why does my weight increase between two dialysis sessions? These are important questions because what you eat and drink can directly affect how your body feels before and after dialysis. The right diet does not mean that you have to stop enjoying food. Instead, it means understanding which foods and drinks need to be limited, how much you can safely consume, and how to follow the fluid and dietary plan recommended by your nephrologist and dietitian. For patients looking for Dialysis in Vijayawada, understanding these dietary precautions is an important part of learning how to manage life during regular dialysis treatment. Why Do Dialysis Patients Need to Control Water Intake? Healthy kidneys continuously remove extra water from the body through urine. When kidney function becomes severely reduced, this natural process is affected. Dialysis can remove some of the excess fluid, but fluid can still accumulate between dialysis sessions. This is why dialysis patients are often advised to follow a fluid restriction based on their individual condition. The exact amount is not the same for everyone. It may depend on urine output, body size, dialysis schedule, heart condition, blood pressure, and other medical factors. Drinking more fluid than recommended can cause the body to retain excess water. This may result in swelling of the feet, ankles, face, or hands. Some people may also notice rapid weight gain between dialysis sessions. When too much fluid accumulates, it can become more difficult for the heart and lungs to handle the extra volume. In some patients, fluid overload can contribute to breathlessness, high blood pressure, and other serious complications. Therefore, fluid restriction is not simply about drinking less water. It is about maintaining a safer fluid balance between dialysis treatments. What Happens If a Dialysis Patient Drinks Too Much Water? Excessive fluid intake between dialysis sessions can lead to a condition commonly described as fluid overload. Since the kidneys cannot remove the extra fluid efficiently, the fluid remains in the body until it can be removed during dialysis. One of the easiest ways to notice excess fluid is through an increase in body weight. This is why dialysis patients are usually weighed before and after dialysis. The weight gained between dialysis sessions is often largely related to fluid accumulation rather than actual body tissue gain. If the increase is significant, removing all of that fluid during one dialysis session may be difficult or may cause uncomfortable symptoms. Large amounts of fluid removal during dialysis can sometimes lead to low blood pressure, cramps, weakness, dizziness, or nausea. For this reason, preventing excessive fluid accumulation is generally better than trying to remove a very large amount of fluid during a single treatment. Important fluid management points for dialysis patients Follow the fluid limit prescribed by your nephrologist rather than following a general number found online. Your appropriate fluid allowance depends on your kidney function, urine output, dialysis schedule, and other health conditions. Remember that fluids include more than plain water. Tea, coffee, milk, juices, soups, ice cubes, soft drinks, and other liquid foods can also contribute to your daily fluid intake. Measure your daily fluids when you have been advised to restrict them. Using a measuring cup or bottle can help you understand how much you are actually consuming instead of estimating. Reduce unnecessary thirst by controlling salt intake. Eating very salty foods can make you thirsty and may encourage you to drink more fluid, making fluid management more difficult. Do not change your fluid restriction suddenly without medical advice. If you are extremely thirsty, producing more or less urine than usual, or experiencing swelling or breathlessness, discuss it with your healthcare team. Why Is Weight Gain Between Dialysis Sessions Important? One of the important measurements for a dialysis patient is the change in body weight between treatments. This is sometimes called interdialytic weight gain. If a patient drinks a lot of fluid between two dialysis sessions, the extra water can increase body weight. A sudden increase may indicate that the body is retaining more fluid than recommended. For example, if your target or dry weight has been established by your dialysis team, a significant increase above that weight may indicate fluid accumulation. Your dialysis team can determine how much fluid needs to be removed during treatment. Patients should not compare their weight goals with another dialysis patient because dry weight and fluid requirements are individualized. The commonly mentioned goal of keeping weight gain around two to three kilograms should not be treated as a universal rule for every person. Your nephrologist should determine the appropriate target based on your medical condition. For anyone undergoing Dialysis in Vijayawada, regular monitoring of weight before and after dialysis can provide useful information about fluid balance and help the healthcare team adjust treatment when necessary. Why Is Potassium Control Important During Dialysis? Potassium is an essential mineral. It helps muscles function properly and plays an important role in maintaining the normal electrical activity of the heart. However, when kidney function is severely reduced, the body may not be able to remove potassium effectively. As a result, potassium can accumulate in the blood. A high potassium level is known as hyperkalemia. In some cases, it may cause muscle weakness, tiredness, nausea, abnormal sensations, or other symptoms. More importantly, very high potassium levels can affect the electrical rhythm of the heart and may lead to dangerous heart rhythm abnormalities. This is why potassium control is particularly important

Translate »